Pages

Showing posts with label Blood Clots. Show all posts

Tuesday, 17 May 2022

Pancreatic Cancer: Four sensations in the leg could be among ‘first clues’ signalling 'lethal' cancer

 THE ILL-DEFINED nature of cancer symptoms can significantly delay referrals, so keeping well-informed of warning signs is crucial. According to recent findings, however, up to 70 percent of cancer patients are unaware of having an increased risk of blood clots. What's more, deep vein thrombosis (DVT) is sometimes the first clue of pancreatic cancer, which is notoriously difficult to treat.

Cancer is a disease of the cells and organs that is fast-spreading by nature. One surefire way to treat the condition is to catch it during the initial stages of its development. But pancreatic cancer, due to its location deep inside the body, is notoriously difficult to pick up at the outset. Four clues in the legs could be among the first signs of the disease, according to health bodies.

Pancreatic cancer has a unique ability to induce blood into a hyper-coagulative state.

In other words, the blood of patients with pancreatic cancer has an abnormal tendency to coagulate, which confers a higher risk of blood clotting.

Therefore, a clot in the leg is sometimes among the first clues that someone has pancreatic cancer, according to the Cancer Society.

“This is called a deep vein thrombosis," explains the health body.

Blood clots may be among the first signs of pancreatic cancer (Image: Getty )

“Symptoms can include pain, swelling, redness and warmth in the affected leg. Sometimes, a piece of the clot can break off and travel to the lungs, which might make it hard to breathe or cause chest pain."

A blood clot that travels to the lungs is medically known as pulmonary embolism or PE, which carries a high mortality risk.

“Still, having a blood clot does not usually mean that you have cancer. Most blood clots are caused by other things,” adds the Cancer Society.

It recently came to the attention of researchers that up to 70 percent of cancer patients are unaware they’re at a higher risk of DVT than the general population.
DON'T MISS:

The discovery emerged from the results of a survey carried out by the European Cancer Patient Coalition (ECPC), which assessed patient awareness and knowledge about cancer-associated DVT.

But aside from the fact that the condition is hard to pick up early, pancreatic cancer is also notoriously difficult to treat.

This makes pancreatic cancer the most lethal cancer in the body, according to Doctor Santhi Swaroop Vege, director of the pancreatic diseases group at Mayo Clinic.

In fact, the disease has an overall five-year survival rate of about seven percent, despite the marked medical advances effectuated in recent years.

CAncer

Symptoms of DVT pain include pain, swelling, redness and warmth in the affected leg (Image: Getty )

The disease is typically characterised by non-specific symptoms, such as weight loss, and abdominal pain, making early detection difficult.

The location of the pancreas in the body also makes it difficult to biopsy or image.

Doctor Vege told News Network: “That’s one of the biggest problems we face. Usually, these people will have indigestion, and acid reflux, before finally somebody thinks of a CT scan."

Indeed, the condition tends to be found at advanced stages when abdominal pain or jaundice has resulted.

Cancer: The signs and symptoms

Cancer: The signs and symptoms to look out for (Image: EXPRESS.CO.UK)

“At that time, it’s already late,” noted Dr Vege.
“If [the cancer] is localised to the pancreas and it is not involving the major structures, then the best treatment, of course, is resection - a big surgery.”
The best way to treat pancreatic cancer, however, is to remove the tumour completely before it spreads to neighbouring regions.
Men have a slightly raised risk of pancreatic cancer compared to women, which has partly been attributed to higher rates of smoking among men.

Monday, 2 August 2021

DW Opinion: Do not write off the AstraZeneca vaccine

The authorities are playing cautiously by freezing AstraZeneca vaccinations. But that doesn't mean that the jab is unsafe, DW's Fabian Schmidt writes.

  • Date 16.03.2021
  • Author Fabian Schmidt
A container with the Oxford-vaccine AZD1222 by AstraZeneca

The AstraZeneca vaccine is on hold in Germany out of an abundance of caution

Yes, two people died from sinus vein thrombosis, and others had to be treated in hospital. And, yes, it happened in both cases after the people had received vaccinations with the Oxford vaccine from Astra-Zeneca. 

But to conclude that the vaccine is dangerous would be entirely premature. First, it is unclear whether the thromboses actually had anything to do with the vaccine.  And secondly, we humans take on much greater risks of thrombosis day after day than we might face as a result of the vaccine.

Cause or correlation?

First, the most important thing: Some people do experience thrombosis — with or without vaccination. Whether it is coincidence or whether there is a causal relationship with vaccination is usually shown by statistics. The question is: Is there an unusual increase of thrombosis cases after vaccination? 

DW science editor Fabian Schmidt

"I will be happily rolling up my sleeve for the Oxford vaccine," DW's Fabian Schmidt says

From what we know so far, that is not the case with the AstraZeneca vaccine. In fact, doctors in the UK alone have already administered more than 11 million doses of the vaccine. Three cases of sinus vein thrombosis have occurred. There have been seven cases in 1.6 million vaccinated people in Germany.

This equates to four cases per million jabs since use of the AstraZeneca vaccine began in Germany in early February. However, this type of thrombosis occurs approximately two to five times per million people per year in the general population even without vaccination.

The cases came from a batch that included a total of 1 million doses. With so many jabs administered, it stands to reason that some people will also experience thrombosis within a certain time frame of vaccination — this may be a coincidence.

Nevertheless, it is right for the regulatory authorities to once again thoroughly examine all study results  and available figures, as many studies have not been fully completed because of the accelerated approval procedures.

A vaccine may protect you against a specific disease, but it won't protect you against  other factors that could cause death. Currently, more very old and seriously ill people are receiving COVID-19 vaccines. People who are already vulnerable may be more likely to die of other causes. 

High risk of thrombosis in everyday life

All of this is no reason to panic: We deliberately take on much higher thrombosis risks elsewhere than they might now — perhaps — come by the way of vaccination. In a well-known and scientifically proved example, for every million women who take the birth control pill, about 1,100 will get thrombosis.

In addition, various circumstances or behaviors  have been shown to double our risk of thrombosis. These include: obesity, travel (especially long-distance flights, car, bus or train rides) and  smoking. 

All of these factors have been clearly proved scientifically. A possible link to vaccinations has not been proved at all.

But we must also consider the following: The sinus vein thromboses that have occurred are considered to be rarer and more dangerous than other forms of thrombosis.

Vaccinations save lives

We are at the beginning of a dangerous third wave  of infection with the coronavirus. For Germany, medical experts are already predicting incidence rates of over 300 per week per 100,000 inhabitants.

All vaccines currently available on the market are shown to work. That means: They prevent severe courses of disease and hospitalization, even with the now-dominant variants.

Vaccinations save lives. And AstraZeneca's vaccine also saves lives.

Given the global spread of the disease, with more than 120 million people now infected and more than 2.6 million deaths, we cannot afford to throw away even a single dose of vaccine.

Each vaccine dose belongs in someone's upper arm. And, when my turn comes, I'll be happy to take the vaccine from AstraZeneca, too. 

DW RECOMMENDS

https://www.dw.com/en/opinion-do-not-write-off-the-astrazeneca-vaccine/a-56888864

Thursday, 29 April 2021

15 Mar 21 Is Europe's AstraZeneca jab decision-making flawed?

A number of countries have decided to suspend use of the Oxford-AstraZeneca vaccine ... "Sometimes it can be harmful to wait for certainty. Not vaccinating people will costs lives."

Nick Triggle
Health correspondent
@nicktriggleon Twitter

Published
Related Topics
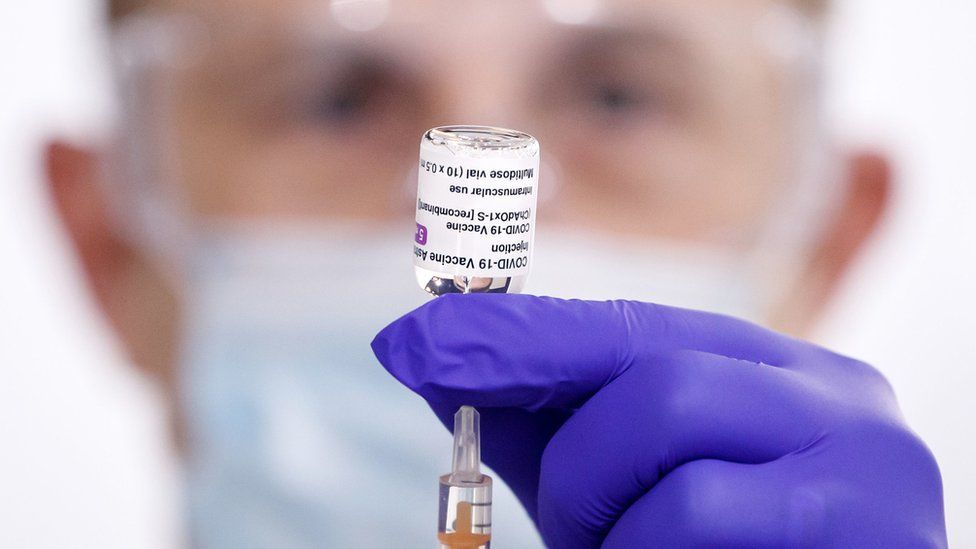
A man holding the Oxford vaccineIMAGE COPYRIGHTPA MEDIA

A number of countries have decided to suspend use of the Oxford-AstraZeneca vaccine as a precaution following reports that some people have suffered blood clots after being given the jab.

But is it a case of being too cautious? Are these nations missing the bigger picture?

The decision has been made on the basis of the precautionary principle - a well-established approach in science and medicine that stresses the need to pause and review when evidence is uncertain.

But in a fast-moving pandemic, when each decision can have major consequences, it is an approach which can sometimes do more harm than good.

Cause or coincidence?

The data supplied by AstraZeneca shows there have been 37 reports of blood clots among the 17m people across Europe who have been given the vaccine.

But the key question that has to be asked is whether this is cause or coincidence? Would these clots have happened anyway?

Adverse events like this are monitored carefully, so regulators can assess if they are happening more than they should.

The 37 reports of clots are below the level you would expect. What is more, there is no strong biological explanation why the vaccine would cause a blood clot.

It is why the World Health Organization and UK drugs regulators have all said there is no evidence of a link.

Even the European Medicines Agency, which is looking into the reports, has suggested the vaccine should continue to be used in the meantime given the risk Covid presents to health.

Unsurprisingly, therefore, the decisions by individual nations to pause their rollouts have baffled experts.

Prof Adam Finn, a member of the WHO's working group on Covid vaccines, says stopping rollout in this way is "highly undesirable" and could undermine confidence in the vaccine, costing lives in the long-term.

"Making the right call in situations like this is not easy, but having a steady hand on the tiller is probably what is needed most."

Has Europe got a problem with the vaccine?

This is not the first time countries in Europe have exercised caution about the AstraZeneca vaccine.

The precautionary principle was adopted by Germany, France and others when they did not initially recommend use of the vaccine for the over-65s. French President Emmanuel Macron even called it "quasi-ineffective".

The over 65s decision has now been reversed, but the impact is still being felt it seems.

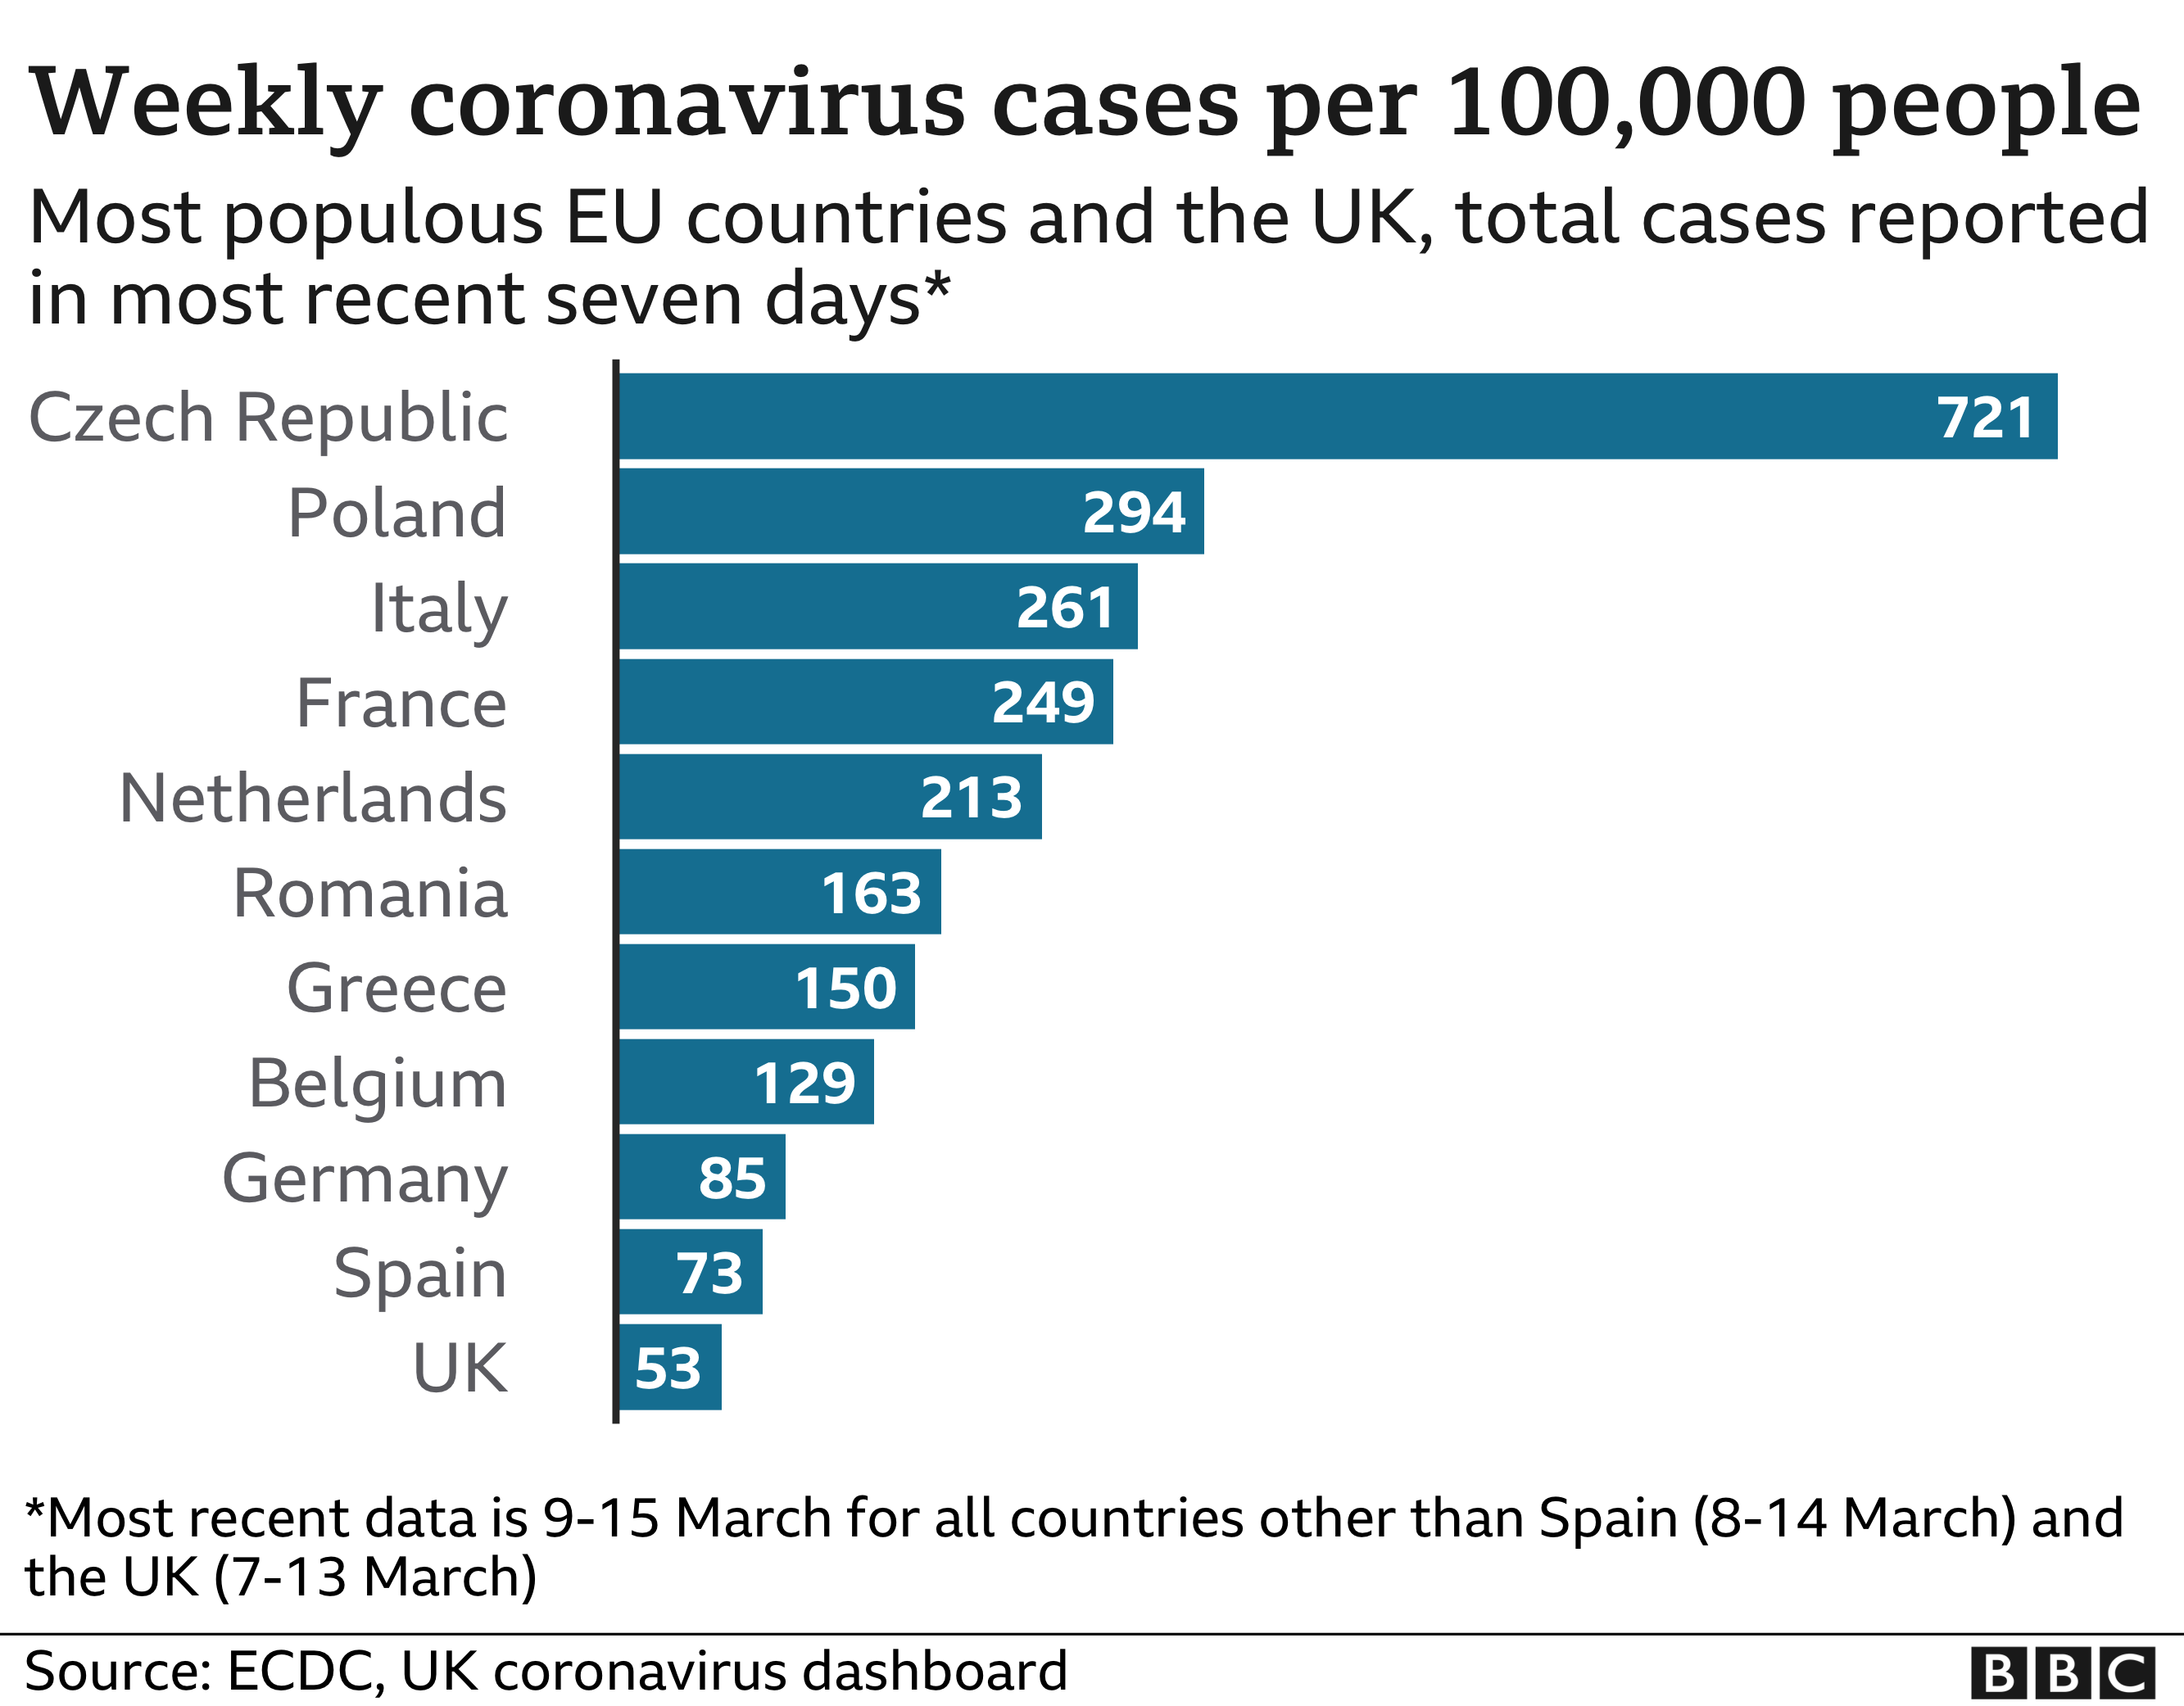
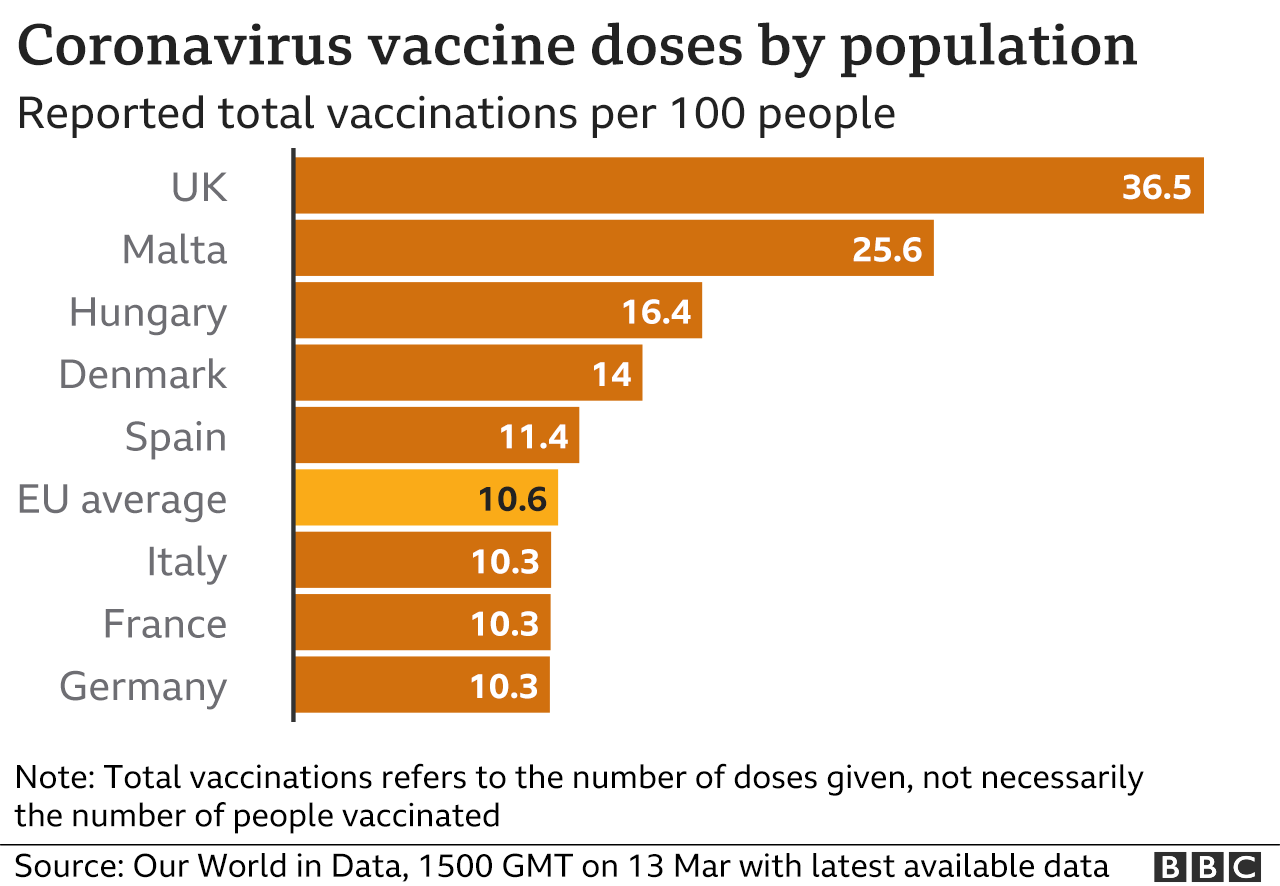
Germany and France have supplies of the vaccine going to waste, with both countries having used fewer than half their supplies of the AstraZeneca jab so far. It has left them far more reliant on the Pfizer vaccine than the UK is.

And this is threatening to have deadly consequences. France, Germany and the other major European nations all have higher rates of infection than the UK, and face the prospect of things getting worse before they get better.

Chart showing infectin rates in EuropeIMAGE COPYRIGHTBBC NEWS
Presentational grey line

If you look back at the decision on the over-65s, you can see how it was made. The way the trials had been organised meant there was limited evidence on its use in older age groups.

The organisers had wanted to recruit younger adults in the initial stages for safety reasons, so when it came to regulators assessing infection rates the data was not yet ready for older people.

But there was evidence from blood samples that the vaccine had prompted a strong immune response in the older age groups. So there was no reason why the vaccine would not work in older age groups - it was just that insufficient time had passed to gather the evidence in the real world.

There was also a problem interpreting results because of the way the trial was run. There was a lack of consistency across the different sites used.

Protocols and practices followed varied across each, including the use of a half-dose in one.

Some have described it as four trials within a trial. It created a somewhat messy set of data to interpret.

Why bold decision-making may be best

The UK looked past this and took the leap though - and within months was reporting "spectacular" results in reduced levels of serious illness in the over-80s.

It was this pragmatic approach to decision-making that also led the UK to recommend up to a three-month gap between doses.

This caused much controversy when it was announced at the end of December.

Chart showing coronavirus doses by population in various European countries.
Presentational grey line

The Pfizer vaccine was not tested like this in trials - the interval was three weeks.

But again, the absence of evidence did not mean the move would not work or was not based on logic.

The AstraZeneca trials did have longer intervals for some participants, which seemed to make it more effective, while evidence on the Moderna vaccine, which is a similar type of jab to Pfizer, also suggested it could work.

It is also well-established that with two-dose vaccines, most of the protection is provided by the first dose, while the second boosts that and provides more long-lasting protection.

With cases rising rapidly at the time, the UK was clear the benefit of maximising available vaccine supplies to provide some protection to more people was the right step even if the trial evidence did not directly support it.

Prof Sir David Spiegelhalter, an expert in understanding risk at Cambridge University, says it shows that sometimes you have to look beyond the precautionary principle and be bold in your decision-making.

"The precautionary principle favours inaction as a way of reducing risk. But the problem is that these are not normal times and inaction can be more risky than action."

What is needed in circumstances like these, according to Sir David, is to work out what is most likely on the balance of probability. That requires looking at both the direct and indirect evidence and the context those decisions are being made in.

"Sometimes it can be harmful to wait for certainty. Not vaccinating people will costs lives."

More on this story

https://www.bbc.com/news/health-56360646